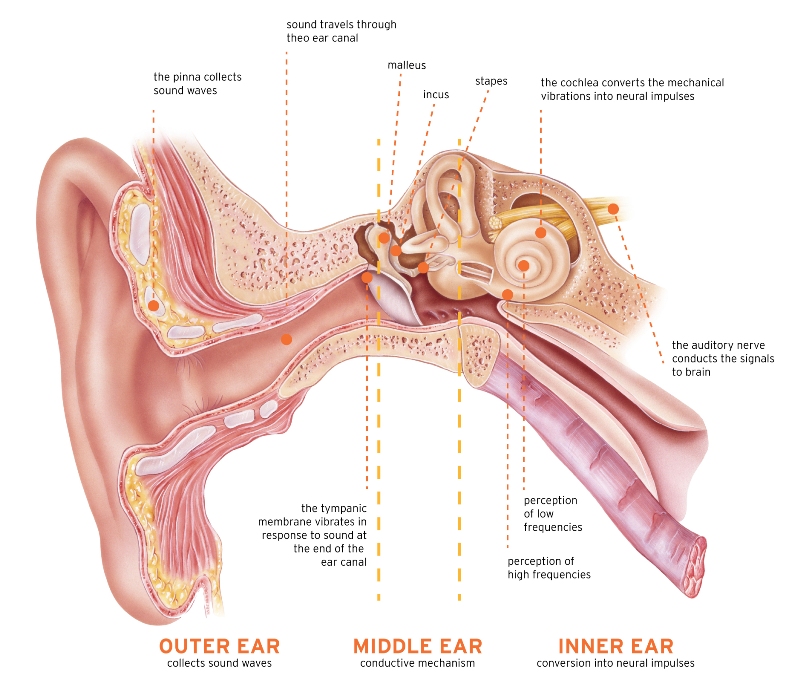
Single-sided deafness means one ear has severe to profound hearing loss that a standard hearing aid cannot improve, while the other ear hears normally. One working ear sounds like it should be enough, but hearing is a two-ear process. You lose the ability to tell where sound is coming from and to separate speech from background noise. CROS systems, bone-anchored devices and cochlear implants can all restore input from the affected side.
If you have lost hearing in one ear, you have probably had some version of this conversation: you explain that you cannot follow conversation in a restaurant, and someone points out that your other ear is fine.
They are not being unhelpful. It is genuinely counterintuitive. But one good ear is not the same as normal hearing, and understanding why is the first step to doing something about it.
What is single-sided deafness?
Single-sided deafness, or SSD, is when one ear has severe to profound hearing loss with little or no usable hearing, and the other ear hears normally or close to it.
It is different from mild or moderate hearing loss in one ear. With SSD the affected ear contributes almost nothing, so the brain is working entirely from one side. It is also sometimes called unilateral hearing loss.
Why one good ear is not enough
Your brain uses tiny differences between what each ear receives to do three things it cannot do with one ear alone.
Locating sound. Sound reaches the nearer ear a fraction earlier and slightly louder. Your brain compares the two and works out direction automatically. With one ear, that comparison is gone, which is why you turn in circles looking for a ringing phone.
Separating speech from noise. Two ears let the brain compare signals and suppress the background, an effect that makes a noisy room dramatically easier to follow. This is the ability people miss most, and it is why restaurants become exhausting.
Hearing around your own head. Your head physically blocks sound coming from the far side, reducing high pitch sounds significantly. With two working ears the far ear picks it up. With SSD, anyone sitting on your affected side is behind a wall.
This is why SSD feels more disruptive than the audiogram suggests. Quiet one-on-one conversation is fine, which makes the condition easy to underestimate, right up until you are at a dinner table.
What causes hearing loss in one ear?
In many cases the loss happens suddenly and without warning.
Sudden sensorineural hearing loss. A rapid loss over hours or days. This is a medical emergency and the single most time-critical cause, because prompt treatment can preserve hearing.
Viral infection. Some viral illnesses damage the inner ear or hearing nerve, causing sudden and permanent one-sided loss.
Acoustic neuroma. A benign tumour on the hearing nerve, usually causing gradual one-sided loss with tinnitus and sometimes unsteadiness. It needs to be ruled out in any unexplained one-sided loss.
Head or ear trauma. Direct damage to the ear or the hearing nerve.
Meniere’s disease. Can progress to significant loss in the affected ear.
Circulatory or autoimmune conditions. Reduced blood flow to the inner ear, or autoimmune inner ear disease.
Complications of surgery or treatment. Certain ear surgeries and, rarely, some medical treatments.
Congenital causes. Some people are born with hearing in one ear only.
Because the causes vary so widely, and because a few of them need medical attention rather than a hearing device, assessment matters before anything else.
What is it actually like day to day?
The pattern is consistent across the clients we see.
- Restaurants, cafes, workplaces and parties become disproportionately hard
- You cannot tell where sound comes from, which is frustrating indoors and a genuine safety issue crossing roads or cycling
- You start seating yourself strategically, putting your good ear towards the group without really deciding to
- You are mentally exhausted after social events, because the brain is filling gaps all evening
- Phone calls on the affected side are impossible, so the phone lives on one side permanently
- You miss things said from your affected side and get a reputation for not listening
The social effect is usually the one that pushes people to act. Constant low-level misunderstanding is wearing, and many people quietly withdraw from group settings rather than explain themselves repeatedly.
Why won’t a normal hearing aid help?
A hearing aid amplifies sound into the ear it sits in. That works when the ear still has usable hearing to amplify into.
With severe to profound loss, there is not enough functioning hearing left for amplification to reach. Making the sound louder does not help if the pathway is not there to carry it. This is why people with SSD are often told nothing can be done, which is out of date.
The modern approach does not try to fix the affected ear. It routes sound from that side to somewhere it can be heard.
What are the options?
CROS hearing aids
CROS stands for contralateral routing of signal, and it is the most common solution.
A CROS is a pair of hearing aids. The device worn on your affected ear works as a microphone only, picking up sound from that side and sending it wirelessly to the hearing aid worn on your good ear, which delivers the sound to you. Your brain now receives information from both sides.
What that means day to day: you hear the person sitting on your affected side. You stop missing half the conversation at a table. You are no longer choosing your seat based on your hearing.
A CROS will not restore true directional hearing, because that requires two working inner ears. What it does restore is access, and for most people that is the difference that matters.
Bone-anchored hearing devices
These transmit sound as vibration through the skull to the better-hearing inner ear, bypassing the affected ear entirely. They come as an implanted device, and also in non-surgical forms worn on a softband or an adhesive adapter, which are often used to trial the sound before anyone commits to surgery.
Cochlear implants
In some cases a cochlear implant can restore hearing in the affected ear itself, rather than routing sound to the other side. This is the only option that can give back genuine two-ear hearing, and candidacy depends on the cause and duration of the hearing loss. It is worth asking about, particularly if your loss is recent.
Accessories and strategies
Remote microphones, TV streamers and a handful of practical habits make a real difference alongside any of the above, and sometimes on their own. If you are not ready for a device, this is a reasonable place to start.
What does it cost, and is there funding?
Devices for single-sided hearing loss are a significant purchase, and the funding question is usually the one people are most reluctant to ask.
Depending on your circumstances there may be support available. The Australian Government Hearing Services Program and Department of Veterans’ Affairs entitlements cover eligible people for hearing devices, the NDIS covers some people under 65, and private health insurance may contribute. Cochlear implants are funded differently again, through the hospital system and private health cover rather than the Hearing Services Program. Payment plans are also an option.
We will go through what applies to you at your appointment, before you make any decisions. Nobody should be choosing a device without knowing what it actually costs them.
What to do next
If your hearing loss in one ear is new or sudden, treat it as urgent and get assessed today rather than this week.
If it is long-standing and you have been told nothing can be done, it is worth a second look. CROS technology has changed considerably, and a proper assessment will tell you what your options are now rather than what they were when you were last told.
Book an assessment for hearing loss in one ear
We will identify the cause, explain what is available, and match the solution to how you actually live rather than to the audiogram alone. That includes an honest conversation about cost and funding.
Call 03 9800 5697 or book an appointment online.